Dental Crowns for Deep Decay: When Fillings Are Not Enough
Most people hope a cavity can be handled with a simple filling, a short appointment, a little numbness, and then life goes on. Sometimes that is exactly what happens. But when decay runs deep, especially when it has hollowed out a large portion of the tooth, a filling may no longer be the restoration that gives the tooth a fair chance. At that point, dental crowns enter the conversation, not as an upsell or a dramatic last resort, but as a practical way to protect what remains.
Deep decay changes the mechanics of a tooth. It is not only about removing soft, infected structure. It is about what is left behind after the decay is cleaned out. A tooth that has lost too much enamel and dentin can still sit in the mouth and look salvageable at first glance, yet be weak enough to crack under everyday chewing. That is where judgment matters. The question is not only, “Can this tooth be filled?” It is, “Will this tooth hold up six months or five years from now?”
Patients often hear the terms filling, crown, root canal, and buildup in the same visit and feel as if the plan escalated very quickly. In reality, those recommendations often come from the same basic issue: the decay has crossed a threshold where patching the hole is not enough. A crown is meant to restore shape, function, and durability when the remaining tooth is too compromised to trust with a filling alone.
What deep decay really does to a tooth
A small cavity is usually a local problem. The decayed area is removed, the space is sealed, and the rest of the tooth does the heavy lifting. Deep decay is different. By the time it reaches the inner dentin, or gets close to the nerve, the tooth often loses a significant amount of structural support. What looks like a single cavity on an x-ray may, once cleaned, turn into a much larger defect than expected.
This surprises patients all the time. A person comes in with mild sensitivity to cold, thinking they need a routine filling. After decay removal, the cavity extends under a cusp or along a sidewall, leaving thin enamel ridges that flex when the patient bites. Those thin walls may survive the appointment, then fracture on a sandwich, a bagel, or a handful of nuts a week later. That is one reason dentists sometimes recommend a crown even before anything is broken. They are trying to prevent the break that experience says is likely coming.
Teeth are strong when their natural architecture is intact. Enamel handles compression well, dentin provides resilience, and the cusps help direct force. Deep decay disrupts all of that. It turns a load-bearing structure into something more like a shell.
Why a filling can fail in a deeply decayed tooth
Fillings are excellent restorations in the right situation. Modern materials bond well and can be very conservative. But they are not magic. A filling replaces missing material. It does not recreate the original toughness of an extensively weakened tooth.
The issue is often one of leverage. If a large part of the chewing surface is missing, or if one or more cusps are undermined, every bite places stress on the remaining walls. A large filling can restore the shape, but the tooth itself may still flex around it. Over time, that leads to cracked enamel, leakage, sensitivity, recurrent decay, or a full fracture.
The problem gets worse when the cavity extends between teeth and below the contact point. In those cases, the restoration has to rebuild not just a hole, but an important part of the tooth’s contour and strength. If too much of the tooth circumference is gone, the filling may act more like a patch on a collapsing structure than a true repair.
Dentists also look at where the tooth sits in the mouth. Back teeth, especially molars, absorb heavy force. A large filling in a front tooth may function well for years because the load is lower and the biting pattern is different. A large filling in a lower first molar has a much harder job.
The moment a crown becomes the better option
There is no single measurement that determines when a crown is necessary, but certain patterns strongly point in that direction. If decay has removed a large portion of the tooth, if one or more cusps are unsupported, if a previous large filling has failed, or if the tooth has had root canal treatment, the balance often tips toward a crown.
A useful way to think about it is this: a filling restores a defect, while a crown restores and reinforces the whole visible part of the tooth. It covers the prepared tooth from the top and around the sides, creating a protective outer layer that helps the tooth withstand chewing forces more evenly.
In practice, several situations commonly lead to the crown discussion:
- The cavity is so large that little healthy tooth remains after decay removal.
- One or more cusps are cracked, undermined, or likely to fracture.
- The tooth already has a very large old filling and recurrent decay around it.
- The tooth has had a root canal and is more brittle or structurally reduced.
- The patient has heavy biting forces, clenching, or a history of breaking teeth.
These are not rigid rules. Clinical decisions still depend on x-rays, direct examination, decay depth, bite pattern, and whether the margins can be kept clean and dry during treatment. But when multiple factors line up, a crown tends to offer the more predictable long-term result.
What a dental crown actually does
A crown is often described as a cap, which is simple but incomplete. It does not just sit loosely over the tooth like a helmet. It is designed to fit precisely over a reshaped tooth and bond or cement into place. Once seated properly, it becomes the new external surface that the patient chews on.
That full coverage matters. Instead of relying on weakened tooth walls to stand on their own, the crown splints the structure together. It redistributes force across the tooth, reducing the chance that a compromised cusp will snap off. In many cases, especially after deep decay, this is the difference between preserving a tooth and watching it fracture beyond repair later.
The effect is easiest to understand with a common scenario. Imagine a lower molar with a deep cavity and an old silver filling that already occupies half the chewing surface. After the decay is removed, only thin walls remain on the tongue side and cheek side. A new filling could replace the lost material, but those thin walls still have to survive years of chewing. A crown, by contrast, reduces and covers those walls, turning a vulnerable shape into a unified structure.
Deep decay and root canal treatment often travel together
Not every deeply decayed tooth needs a root canal, but the two issues often overlap. When bacteria get close to or into the pulp, the nerve tissue can become inflamed or infected. Symptoms vary. Some people feel lingering cold pain, throbbing, pain when biting, or spontaneous toothaches that wake them at night. Others have very little pain and are surprised to learn the nerve is involved.
If root canal treatment is needed, the case for a crown usually becomes stronger, particularly in back teeth. A root canal-treated tooth is not dead in the dramatic sense people sometimes imagine, but it has lost its internal pulp tissue and is often more prone to fracture because it is already structurally compromised. In many cases, the cavity that led to the root canal was large to begin with, and the access opening for treatment removes a bit more internal support.
This is why a dentist may say, “The root canal solves the infection, the crown protects the tooth.” They address different problems. One deals with the inside of the tooth, the other with the outside.
Why waiting can make a manageable problem worse
Patients sometimes delay crowns because the tooth stops hurting after the initial treatment, or because the temporary filling feels fine. That is understandable. If symptoms ease up, urgency fades. But symptom relief does not necessarily mean the tooth is strong.
A weakened tooth can break quietly at first. A corner fractures off. A crack forms under the gumline. The temporary restoration leaks. Recurrent decay creeps under the margins. In some cases, a tooth that could have been crowned becomes a tooth that needs extraction because too little sound structure remains.
One of the harder conversations in dentistry is with someone who postponed the crown on a salvageable tooth, then returns months later with a split molar. There is often no dramatic event. They bit on toast, or nothing memorable at all. The fracture just finally declared itself. From the patient’s perspective, it feels sudden. From a structural standpoint, it had been developing for some time.
What the appointment process usually looks like
For a standard crown, the tooth is numbed, decay or old filling material is removed, and the tooth is reshaped so the crown has room and retention. If the cavity is very deep or irregular, the dentist may first place a buildup, which is a foundation material used to replace missing internal structure. That buildup is not the final restoration. It helps create a stable form for the crown to fit over.
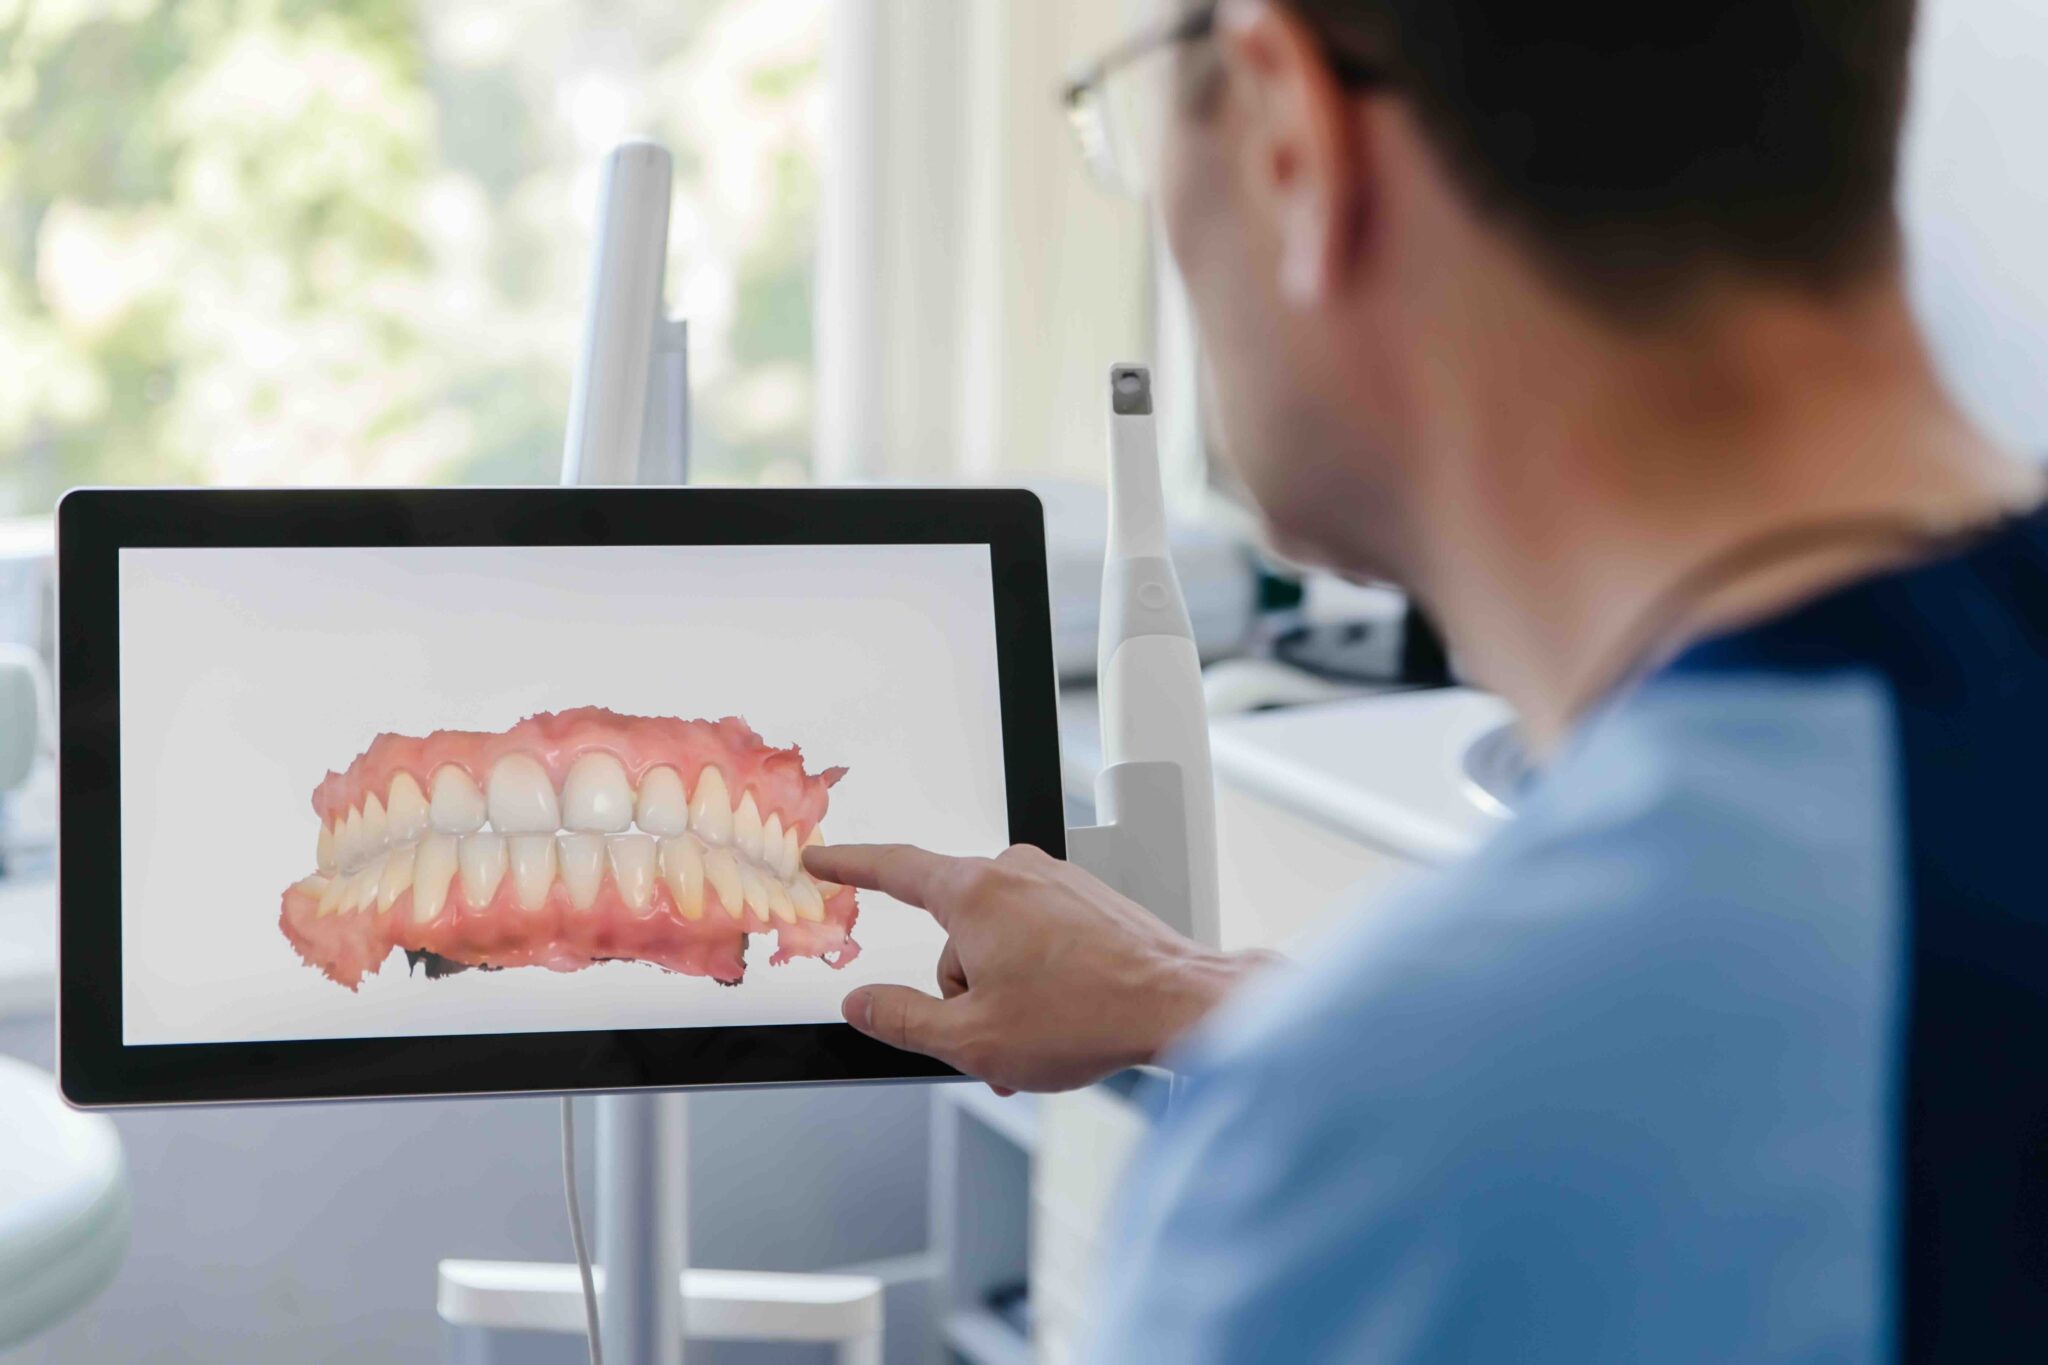
After preparation, the dentist takes a digital scan or impression. A temporary crown is often placed while the final crown is made in a lab, unless the office provides same-day crowns. The temporary matters more than many patients realize. It protects the tooth, maintains spacing, and lets the gums stay in a healthy position.
When the final crown returns, the fit, contact with neighboring teeth, and bite are checked carefully. Small bite discrepancies can make a crown feel high and irritating, so that adjustment phase is important. When all looks right, the crown is cemented or bonded in place.
There are edge cases. If decay extends too far below the gumline, the tooth may need crown lengthening, which is a procedure to expose more tooth structure. If the remaining tooth is extremely short or broken down, a post may be discussed after root canal treatment, though posts are not used routinely in every case. The best plan depends on how much tooth remains and how forces hit that tooth in function.
Materials matter, but the preparation matters more
Patients often focus on whether the crown will be porcelain, zirconia, porcelain fused to metal, or gold. Those choices matter, especially for appearance, wear characteristics, and where the tooth sits in the mouth. But longevity often depends just as much on basic fundamentals: clean margins, enough thickness, proper bite, and good moisture control during the procedure.
Zirconia has become popular for posterior crowns because it is strong and can work well in heavy-bite situations. Porcelain-based options can look more natural, especially in visible areas. Gold remains an excellent material functionally, even if fewer patients choose it for cosmetic reasons. Each has trade-offs. A very esthetic material may require different handling than a more forgiving high-strength option. A skilled clinician weighs the material against the tooth’s location, the patient’s bite, the amount of clearance available, and the patient’s expectations.
No crown material rescues poor hygiene or a bad seal. Decay can still form at the edge of a crown if plaque sits there consistently. Crowns do not make a tooth immune Dental Crowns to cavities. They protect structure, but they still rely on the surrounding tooth and gum tissue staying healthy.
What a dentist is evaluating behind the scenes
From the patient chair, the recommendation may sound simple: “This tooth needs a crown.” Behind that sentence is a layered assessment. The dentist is considering how much healthy tooth is left above the gumline, whether the margins can be placed on solid enamel or dentin, whether the tooth can be isolated during bonding if needed, how close the decay is to the pulp, whether the patient has a habit of grinding, and whether the bite puts unusual stress on that area.
A heavily restored upper premolar, for example, often fractures differently than a lower molar. Premolars can act like wedges and are notorious for splitting when large fillings undermine both cusps. A molar may hold on longer because it has broader bulk, but once it cracks deeply, the damage can be extensive. Those distinctions rarely make it into a short insurance summary, yet they influence why one tooth gets a crown recommendation sooner than another.
Radiographs help, but they do not tell the whole story. X-rays can underestimate the true spread of decay, especially when old restorations obscure details. Sometimes the final decision is made only after the dentist removes the decayed portion and sees what remains. This is one reason treatment plans occasionally change mid-procedure. It is not indecision. It is that the real condition of the tooth is finally visible.
Cost, insurance, and the value question
Crowns cost more than fillings. That is a real consideration, and it should not be brushed aside. For many patients, the financial difference is significant. Insurance may help, but plans vary widely in waiting periods, annual maximums, downgrades, and material limitations.
The more useful question is often not “Which is cheaper today?” but “Which is more likely to avoid repeat treatment?” A large filling that fails within a year, followed by an emergency visit, pain, additional treatment, or eventual extraction, is not necessarily the economical choice even if the first bill was lower. That does not mean every large cavity needs a crown, or that crowns always last perfectly. It means the decision should account for prognosis, not just the immediate fee.
A good dentist should be able to explain the difference in expected performance. Sometimes they will say a filling is possible but guarded, and a crown is more predictable. That kind of candor is valuable. It gives the patient a real choice rather than a simplified sales pitch.
Recovery and what patients typically notice
After a crown preparation, it is common to have mild gum soreness and temporary sensitivity, especially to cold or pressure, for a few days. The temporary crown can feel slightly different from the natural tooth, and flossing may need a gentler technique to avoid pulling the temporary off. Once the final crown is placed, most patients adapt quickly if the bite is balanced well.
There are times when follow-up is needed. If a crown feels high, even by a tiny amount, the tooth can become sore with chewing and the jaw can feel off. If cold sensitivity lingers beyond the expected period, the pulp may still be irritated from the original deep decay or from the procedure itself. Occasionally, a tooth that seemed borderline stable will later declare a need for root canal treatment. Deep decay is not always fully predictable, even with careful work.
That uncertainty is worth saying plainly. A crown improves structural prognosis, but it cannot rewind the history of a tooth that has already been heavily damaged. The goal is to preserve and strengthen what remains as reliably as possible.
How to care for a crowned tooth long term
Once the final crown is in place, the maintenance principles are familiar but important. Brush thoroughly at the gumline, clean between the teeth every day, and do not assume the crown itself can decay, so the area is maintenance-free. The vulnerable zone is the margin where crown meets tooth. That is where plaque sits, where recurrent decay begins, and where cement can fail if hygiene is neglected.
For patients who clench or grind, a night guard can make a major difference. This is especially true if multiple teeth already show wear or if previous restorations have chipped. It is frustrating to invest in a strong restoration and then subject it to repeated nighttime overload.
The basics matter most:
- Keep the crown margins clean with brushing and interdental cleaning.
- Return for periodic exams and x-rays so hidden decay or bite issues are caught early.
- Report chewing pain, a high bite, or a loose feeling instead of waiting.
- Use a night guard if grinding is part of the picture.
- Limit habits that crack teeth, such as chewing ice or opening packages with teeth.
These habits do not guarantee a crown will last forever, but they improve the odds considerably.
When a crown is not the right answer
Not every badly decayed tooth should be crowned. Sometimes the decay extends so far below the gumline or into the root that the tooth cannot be restored predictably. Sometimes a vertical root fracture is already present, in which case a crown would only cover a tooth that is structurally doomed. In other situations, the remaining tooth is too short, the surrounding bone support is poor, or the patient’s overall treatment plan points toward extraction and replacement instead.
There are also cases where a large bonded onlay or partial coverage restoration may work well instead of a full crown. These restorations can preserve more natural tooth in selected situations, particularly when the margins are favorable and enough strong enamel remains. The right choice depends on the tooth, the bite, the material, and the operator’s experience. “Crown or filling” is not always the only fork in the road.
Still, for many teeth with deep decay, the practical decision is between a restoration that merely fills a hole and one that gives the tooth a realistic chance under load. That is why Dental Crowns remain such a common recommendation in restorative dentistry. They are not a cure-all, and they are not needed for every cavity. But when decay has hollowed out too much of the tooth, a crown is often the treatment that turns a fragile remnant into a functioning tooth again.
The heart of the decision is simple even if the details are technical. Dentists are trying to save the tooth you have, not just for the next week, but for the years when you expect to chew without thinking about it. When fillings are no longer enough, a well-made crown is often the restoration that respects both biology and physics.
Simple Dental Vermont
Address: 8914 S Vermont Ave, Los Angeles, CA 90044
Phone number: +13239493000
FAQ About Dental Crowns
How much do crowns cost per tooth?
In the United States, a single dental crown typically costs between $800 and $2,500 per tooth without insurance. The ultimate out-of-pocket price depends heavily on the crown material, the location of the tooth, and whether you have dental insurance coverage.
What is the downside of crowns on teeth?
The primary downside of a dental crown is that the procedure permanently removes natural tooth enamel to shape the tooth for the cap.
Why do dentists push for crowns?
Dentists recommend crowns because a large filling cannot provide enough strength when a tooth loses a major portion of its structure or faces heavy chewing pressure.